Female Infertility: Causes & Tests
The single most useful thing to know: infertility in females is a medical condition, not a verdict. In many couples an evaluation identifies contributing causes, and treatment options exist for many of them, though in some couples no specific cause is found even after complete testing.
At Blossom Women Wellness Clinic in Vaishali Nagar, Jaipur, Dr. Sunita Choudhary runs a structured fertility evaluation: a clear timeline, only the tests your history calls for, results explained without jargon, and a treatment plan shaped around you.
This article provides general health information. For a fertility assessment in Jaipur, book a consultation on +91 9928070006.
What is Female Infertility?
To define female infertility precisely: difficulty conceiving despite regular, unprotected intercourse for the time thresholds above. Doctors also classify it by history:
| Category | Meaning |
|---|---|
| Primary infertility | A woman has never conceived despite trying |
| Secondary infertility | A woman has conceived before (a previous pregnancy, sometimes ending in miscarriage) but cannot conceive again |
Secondary infertility surprises many couples, a previous pregnancy does not guarantee the next, because tubes, ovulation, sperm counts and age can all change between pregnancies.
When Should You Actually See a Doctor?
The calendar rule is simple:
- Under 35: try for up to 12 months before a formal evaluation.
- 35 or older: seek evaluation after 6 months, fertility generally declines faster here, so time matters more.
- Any age, go sooner if cycles are irregular or absent, if PCOS or endometriosis is already diagnosed, if there is a history of pelvic infection, tuberculosis, ectopic pregnancy or previous surgery on the tubes, or if periods have stopped after stopping contraception.
Waiting a full year with clearly irregular cycles is time lost, not prudence. Women with PCOS, for instance, often have an ovulation problem that can be treated, getting pregnant with PCOD is possible for many, but usually only once ovulation is addressed deliberately.
Signs of Female Infertility: When to Get Evaluated
There is no single “sign you can’t get pregnant”, most women with fertility problems feel completely healthy. What follows are not proof of infertility; they are findings that warrant a gynaecological evaluation, because each can point to a treatable reason why conception is taking longer:
- Irregular or absent periods, the most direct clue to ovulatory dysfunction, which has several treatable causes including PCOS and thyroid disorder.
- Cycles shorter than 21 days or longer than 35 days, ovulation may be unpredictable.
- Very painful periods, painful intercourse, or heavy bleeding, symptoms sometimes associated with endometriosis, fibroids or adenomyosis, which deserve assessment in their own right.
- Periods that do not return within about three months of stopping contraception, worth checking rather than waiting.
- Two or more miscarriages, recurrent pregnancy loss is investigated as part of fertility care.
- Acne, excess facial hair and weight gain together with irregular cycles, a pattern consistent with PCOS that a doctor can confirm or rule out with simple tests.
One caution: symptoms in points 3 and 6 are common in women who conceive without difficulty. They justify an evaluation, they do not by themselves mean anything is wrong.
Who is more likely to face difficulty conceiving? Women over 35, women with diagnosed PCOS or thyroid disease, those significantly under- or overweight, smokers, and women with a history of pelvic infection, tuberculosis, endometriosis or prior tubal pregnancy. If several of these describe you, book the evaluation early rather than waiting out the calendar.
Major Causes of Female Infertility
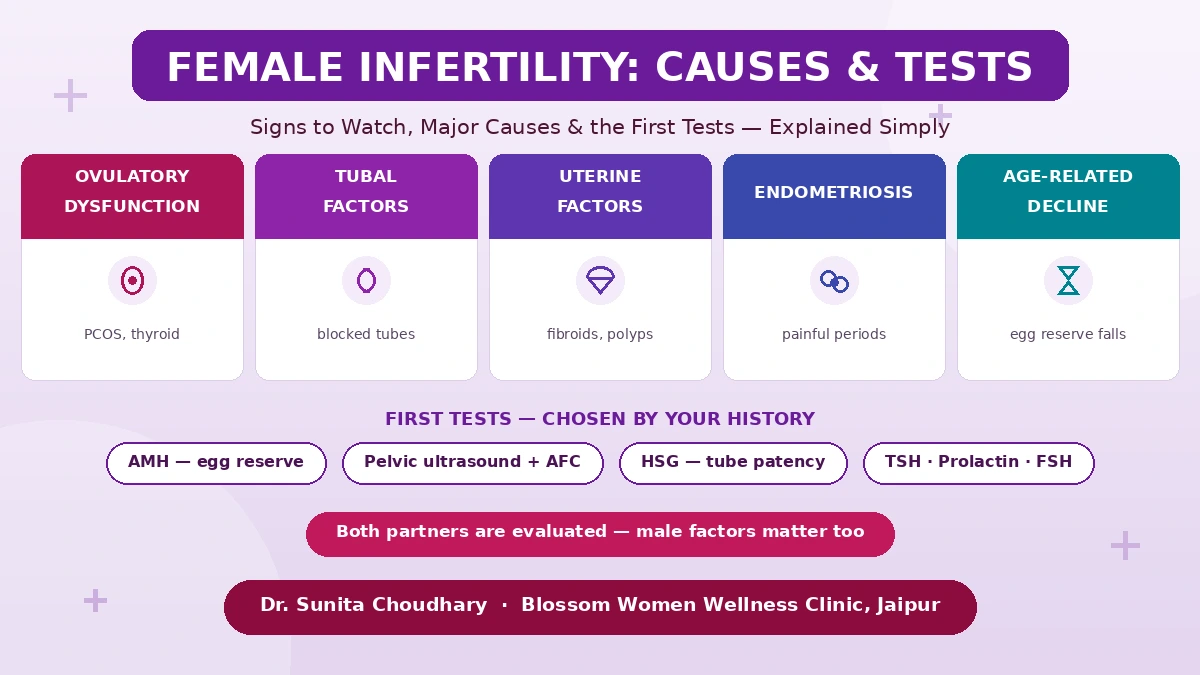
Textbooks and guidance bodies commonly group the female reasons for infertility into five major categories. The relative contribution of each varies between populations, but the grouping looks like this:
| Category | What Goes Wrong | Typical Clues |
|---|---|---|
| Ovulatory dysfunction | Eggs are not released regularly, causes include PCOS, thyroid disorder, high prolactin and reduced egg reserve | Irregular or absent periods, hormonal imbalance symptoms |
| Tubal factors | Fallopian tubes blocked or damaged, old pelvic infection, TB, adhesions after surgery or appendicitis | Often silent; sometimes pelvic pain or history of ectopic pregnancy |
| Uterine factors | Fibroids (especially those distorting the cavity), polyps, adhesions inside the uterus | Heavy or irregular bleeding, recurrent miscarriage, or no symptoms at all |
| Endometriosis | Uterine-lining tissue grows outside the uterus, potentially affecting ovaries, tubes and pelvic environment | Painful periods, pain during intercourse, chronic pelvic pain |
| Age-related decline | Egg quantity and quality both fall, gradually through the 30s, more steeply after 37 | Age itself; tests may show lower AMH and antral follicle count |
Two of these categories deserve a note.
Ovulatory dysfunction is the category most often cited as a leading contributor in population studies, and PCOS is a common cause of ovulatory dysfunction, though not the only one, and its share varies by population. The encouraging part: once a specific ovulation problem is identified, it is often manageable. If your cycles have never been regular, start with our PCOD symptoms and care guide and the FAQ-style PCOS myths and fertility explainer; irregular periods themselves deserve evaluation, as covered in irregular periods: causes and care.
Age is the one factor no treatment reverses: the pool of eggs a woman is born with never replenishes, and both quantity and quality decline with age, slowly through the early 30s, more quickly after 37. That is a reason to seek evaluation sooner with age, not a prediction about any individual woman; plenty of pregnancies happen in the late 30s and beyond.
Regular Periods but Not Getting Pregnant?
This is one of the most searched, and most quietly frustrating, situations: reason for not getting pregnant when everything is normal. The periods arrive on time, the lifestyle is healthy, and still no pregnancy.
Regular periods are reassuring, they usually mean ovulation is happening. But conception needs several things to work at once:
- Regular ovulation, usually present when periods are regular.
- Open tubes, the egg and sperm must meet inside the tube; blocks are silent and only visible on an HSG.
- Healthy sperm, male factors, alone or alongside female factors, are estimated to be involved in roughly half of couples; a regular cycle in the female partner does not check this box.
- A receptive uterus and good egg quality, polyps, cavity-distorting fibroids, and age-related egg changes can all sit quietly behind normal periods.
When the standard evaluation comes back normal, doctors call it unexplained infertility, it accounts for a meaningful share of couples. “Unexplained” does not mean untreatable, and it does not mean there is only one path forward. Management is individualised: it depends on the woman’s age, how long the couple has been trying, whether there have been previous pregnancies, and the couple’s own preferences, ranging from continued timed attempts, to ovarian stimulation, to IUI or IVF.
Tests for Infertility in Females
There is no fixed test package for everyone. Which tests for infertility in females are done, and in what order, depends on each woman’s history, cycle pattern, symptoms and examination findings. The tests below are the ones most commonly used, not a checklist every patient needs.
Female infertility blood tests
- AMH (anti-Müllerian hormone), a blood test that helps estimate the ovarian egg reserve, valid on any day of the cycle. It can also help predict how the ovaries are likely to respond to stimulation during treatment. What it does not do: measure egg quality, or predict on its own whether a woman will conceive naturally, a low value is a planning input, never a verdict.
- Selected hormone tests, FSH, LH and oestradiol (typically drawn early in the cycle), TSH and prolactin are ordered when the history points to them (irregular cycles, symptoms of thyroid or prolactin problems, suspected ovulatory dysfunction). They are not universal screening tests that every evaluation requires; TSH and prolactin are, however, common early additions because thyroid and milk-hormone disturbances are frequent, silent and treatable contributors.
Scans and tube tests
- Pelvic ultrasound (with antral follicle count), often recommended as part of the initial assessment: it counts the small resting follicles, examines the uterus for fibroids or polyps, and looks at the ovaries; it is also part of confirming a PCOS pattern.
- HSG (hysterosalpingography), an X-ray with dye showing whether the fallopian tubes are open and the uterine cavity is normal. This is recommended when tubal factor is a realistic possibility (history of infection, ectopic pregnancy, previous surgery, or unexplained difficulty) rather than for everyone automatically. Done after the period ends, before ovulation; a few minutes of cramping, no anaesthesia.
For the partner
- Semen analysis, count, movement and shape of sperm. Because male factors, alone or alongside female factors, are estimated to be involved in roughly half of couples, this is commonly among the first tests ordered, a genuine fertility test for couples, running both tracks in parallel.
The consultation itself
Bring your last period date, a 3–6 month cycle record, previous reports, and a list of current medicines. Your doctor will use the first consultation to decide which, and how many, of the above tests your situation actually calls for.
Treatment of Female Infertility: The Options
The treatment of female infertility is not a fixed ladder climbed step by step. The right approach depends on the cause found, the woman’s age, how long the couple has been trying, previous treatments, and their preferences, and appropriate treatment sometimes skips a step entirely. The options below are the building blocks:
- Lifestyle measures, for women with PCOS and higher body weight, studies show that weight reduction of even 5–10% can improve ovulation and metabolic markers, though results vary between individuals; stopping smoking, moderating caffeine and starting folic acid are standard advice. This is the best-evidenced first step for many couples, and the reason to complete an evaluation before spending money elsewhere. Ayurvedic and herbal preparations are widely marketed for female infertility, but robust clinical evidence for most is limited; the main risk is not the preparation itself, it is the months lost while a specific, treatable cause, a blocked tube, a thyroid disorder, anovulation, goes unevaluated. Get tested first; then choose with full information.
- Ovulation induction, tablets such as letrozole or clomiphene, with ultrasound tracking, may be recommended when anovulation is confirmed, particularly with PCOS.
- Treating what is found, thyroid or prolactin correction; laparoscopic treatment for endometriosis; hysteroscopic removal of polyps or cavity-distorting fibroids. Sometimes treating the found problem is all that is needed.
- IUI (intrauterine insemination), prepared sperm placed directly into the uterus at ovulation. It may be suggested for mild male factors, unexplained infertility or alongside ovulation induction, depending on the couple’s situation. (IUI vs IVF in one line: IUI assists the natural process inside the body; IVF fertilises the eggs outside it.)
- IVF, may be recommended when, weighing age, diagnosis, ovarian reserve, previous treatment history and personal preferences, simpler approaches are unlikely to succeed, for example with bilateral tubal blockage or severe endometriosis.
Counselling is part of the treatment, not an optional extra. The grief of trying month after month is real, it affects both partners, and it is not a weakness, research finds fertility distress is common among couples, and support (a counsellor, a doctor who explains rather than rushes, structured patient groups) helps many couples stay the course and make clearer decisions.
Guidance Referenced
- WHO, Infertility fact sheet (prevalence and definitions): who.int/news-room/fact-sheets/detail/infertility
- ASRM, American Society for Reproductive Medicine, clinical guidance on infertility evaluation and ovarian reserve testing: asrm.org
- ACOG, American College of Obstetricians and Gynecologists, infertility patient resources: acog.org
Investigation and treatment are always individualised, follow your doctor’s assessment of your specific situation.
Fertility Evaluation in Vaishali Nagar, Jaipur
Trying to conceive without answers? Book a fertility assessment with Dr. Sunita Choudhary at Blossom Women Wellness Clinic, both partners evaluated, results explained plainly.
- Address: 10A, Gate No 4, Shiv Path, near SDC Aishwarya Heights, Nemi Nagar Extension, Block A, Vaishali Nagar, Jaipur, Rajasthan 302021
- Call / WhatsApp: +91 9928070006
- Consultations available in: English and Hindi
This article provides general medical information only and does not constitute a formal diagnosis or personalised treatment plan. For individual medical advice, please schedule a consultation.
Dr. Sunita Choudhary
MBBS, MS (Obstetrics & Gynaecology), FOGSI Member
Senior Consultant Gynecologist & Obstetrician
Blossom Women Wellness Clinic, Vaishali Nagar | Shalby Multi-Speciality Hospital, Jaipur
This article is general health education, not personalised medical advice. For guidance specific to your case, book a consultation on +91 99280 70006 or message on WhatsApp.